The Lung Cancer Screening Gap: Why Some Women Still Fall Outside the Rules

Marsha Sakamaki • October 7, 2026

Short notes on health, aging, and prevention.
No noise. No selling. Ever.

Get TWC Health Notes

Share this Resource:

My OpEd on this topic appeared in the Honolulu Star-Advertiser on December 11, 2025. This expanded version includes newer research and clarifies the difference between screening recommendations and insurance coverage.

Older Asian woman beside an illustrative lung scan, highlighting gaps in lung cancer screening eligibility and coverage.

I always assumed lung cancer screening worked much like other familiar screenings. You reach a certain age, discuss it with your doctor, and get tested. I knew there were details and exceptions, but I hadn’t realized how heavily lung cancer screening depends on your smoking history.


Then I learned something that made the issue personal. I quit smoking in 1996 after years of heavy use. Under Medicare’s national preventive lung cancer screening coverage rules, that quit date puts me outside eligibility.


While researching that gap, I encountered another: Asian women who’ve never smoked generally don’t qualify under standard smoking-based screening criteria. Yet a U.S. research study screened 1,000 of these women and found 13 invasive lung cancers.


These are two different situations with a shared concern. People can fall outside screening rules even when meaningful risk remains. Understanding why requires separating three things that are often treated as interchangeable: your risk, medical recommendations, and insurance coverage.


Two different gaps in lung cancer screening


The first gap affects people like me: former smokers who quit decades ago. Our smoking history may support a screening recommendation, but the time since quitting can exclude us from Medicare’s preventive screening coverage.


The second affects people whose risk isn’t captured by smoking history. This includes Asian women who’ve never smoked, a population receiving increased research attention.


Neither situation means everyone in these groups should automatically receive a scan. But both raise an important question: are the eligibility rules identifying everyone likely to benefit?


My story: I quit in 1996, but the coverage rules still matter


Quitting smoking was one of the best decisions I made for my health. It reduced my risk compared with continuing to smoke. But it didn’t erase the years I’d already smoked.


Medicare covers annual preventive lung cancer screening with low-dose CT for people who meet all its eligibility requirements. Those include:


  • Being ages 50–77.
  • Having no signs or symptoms of lung cancer.
  • Having at least a 20 pack-year smoking history.
  • Currently smoking or having quit within the past 15 years.
  • Receiving an order from a healthcare provider, with a counseling and shared decision-making visit before the first screening. www.cms.gov

A pack-year describes cumulative smoking exposure. One pack a day for 20 years equals 20 pack-years. Two packs a day for 10 years also equals 20 pack-years.


My 1996 quit date falls well beyond Medicare’s 15-year limit. That excludes me from its national preventive screening coverage, regardless of whether my previous smoking exposure meets the pack-year requirement.


However, the American Cancer Society removed the quit-year limit in 2023. It recommends annual screening for people ages 50–80 who currently smoke or previously smoked and have at least 20 pack-years. Individual health, expected benefit, and willingness and ability to receive treatment also matter. www.cancer.org


The U.S. Preventive Services Task Force still uses the 15-year quit limit, along with ages 50–80 and at least 20 pack-years. www.cdc.gov


That means someone with my history could meet the American Cancer Society’s recommendation while falling outside Medicare’s preventive coverage criteria.


A medical recommendation and an insurance coverage decision aren’t necessarily the same thing.


Why the 15-year boundary deserves attention


Your risk doesn’t abruptly disappear on the fifteenth anniversary of quitting. Quitting reduces risk, but aging influences it too.


Research that helped inform the American Cancer Society’s updated recommendation examined those two forces together. The investigators found that absolute lung cancer risk could rise as former smokers aged beyond 15 years since quitting. That finding challenged an automatic stopping rule based only on time since cessation. pmc.ncbi.nlm.nih.gov


A German study published in April 2026 also found that lung cancer mortality risk remained elevated among former smokers after long-term cessation. It supported further consideration of screening eligibility for some older former smokers, although its findings don’t directly establish U.S. screening rules. link.springer.com


For me, the point isn’t that quitting failed to help. It helped enormously. The question is whether elapsed time since quitting should end the screening conversation without considering age, previous exposure, overall health, and potential benefit.


Asian women who’ve never smoked face a different gap


The other issue begins with a different assumption: that someone who never smoked is unlikely to need a conversation about lung cancer.


Smoking remains a major cause of the disease, but people who’ve never smoked develop lung cancer too. Research has identified elevated lung cancer incidence among Asian American women who’ve never smoked, with differences among ethnic groups.


A commentary in the Journal of the National Cancer Institute describes this emerging disparity and the limited knowledge about contributing factors specific to Asian American women. Researchers are investigating family history, environmental exposures, genetic susceptibility, and other possible influences. Findings from women living in Asia don’t necessarily apply in the same way to women living in the United States. pubmed.ncbi.nlm.nih.gov


Asian women aren’t one uniform risk group. Ancestry, exposures, family history, and other circumstances vary. But smoking-based screening rules generally exclude women who’ve never smoked, even when other factors may warrant closer attention.


That makes this a relevant subject for Hawai‘i, where many families have Asian ancestry.


What happened when researchers screened these women?


The U.S. Female Asian Nonsmoker Screening Study, known as FANSS, examined low-dose CT screening in Asian women ages 40–74 who’d never smoked.


Results reported in September 2025 found 13 invasive lung adenocarcinomas among 1,000 women screened, a detection rate of 1.3 percent. Nine were diagnosed at stage IA, an early stage. www.iaslc.org


These women didn’t meet standard smoking-based screening criteria. They were screened through research.

We can’t say they would never have received a scan otherwise. Some might eventually have undergone diagnostic imaging because of symptoms or another finding. But the research identified cancers in a group outside routine smoking-based screening eligibility.


At first glance, 13 out of 1,000 may sound small. The context makes it more meaningful.


In the National Lung Screening Trial, the major U.S. trial involving current and former heavy smokers, approximately 11 cancers were diagnosed per 1,000 people at initial low-dose CT screening, a rate of 1.1 percent. That population included both women and men. pmc.ncbi.nlm.nih.gov


The FANSS investigators themselves highlighted this benchmark. Their study found a detection rate comparable to that of a heavy-smoking population already considered appropriate for screening.




Separate studies found 13 lung cancers per 1,000 Asian women who never smoked and about 11 per 1,000 heavy smokers.

This comparison doesn’t prove Asian women who’ve never smoked have equal or greater risk than heavy smokers. The studies differed in age ranges, participant selection, and methods.


It does explain why the finding deserves attention. A substantial smoking history wasn’t necessary for researchers to find invasive cancers at a rate comparable to a recognized screening population.


What the findings establish, and what remains unanswered


FANSS demonstrates that screening can detect invasive lung cancer among Asian women who’ve never smoked. It also shows that some of those cancers can be found early.


It hasn’t yet established how much routine screening reduces deaths in this population. Researchers still need to determine who benefits most, when screening should begin, how frequently it should occur, and how uncertain findings should be managed.


Newer evidence from Taiwan adds context. A study published in May 2026 examined national lung adenocarcinoma patterns alongside information about self-initiated CT screening. Early-stage diagnoses increased, while advanced-stage incidence declined in selected groups but remained largely stable overall.


Mortality also declined. Because it was observational, the study couldn’t determine how much of the change resulted from screening rather than treatment advances or other factors. pmc.ncbi.nlm.nih.gov

These findings support continued investigation. They don’t establish that every Asian woman needs annual CT screening.


Why screening needs careful follow-up


Low-dose CT screening has reduced lung cancer deaths in trials involving people with substantial smoking histories. www.cancer.gov


However, a scan can also find nodules that aren’t cancer. Some require monitoring or additional procedures. Screening can identify cancers that would never have caused illness during someone’s lifetime, leading to unnecessary treatment. www.cdc.gov


The challenge is to identify people likely to benefit and handle findings appropriately. A useful screening program needs both.


That’s why the next question goes beyond whether cancers can be found. It asks whether a well-designed program improves outcomes enough to justify its costs and potential harms.


Screening and diagnostic evaluation are different pathways


This distinction is especially important for anyone who falls outside screening criteria.


Screening looks for disease before symptoms appear. Being symptom-free doesn’t qualify you by itself. Your age and risk history must also meet the applicable criteria.


Diagnostic evaluation investigates a concern. That might be a symptom, an abnormal examination finding, or something discovered on another test.


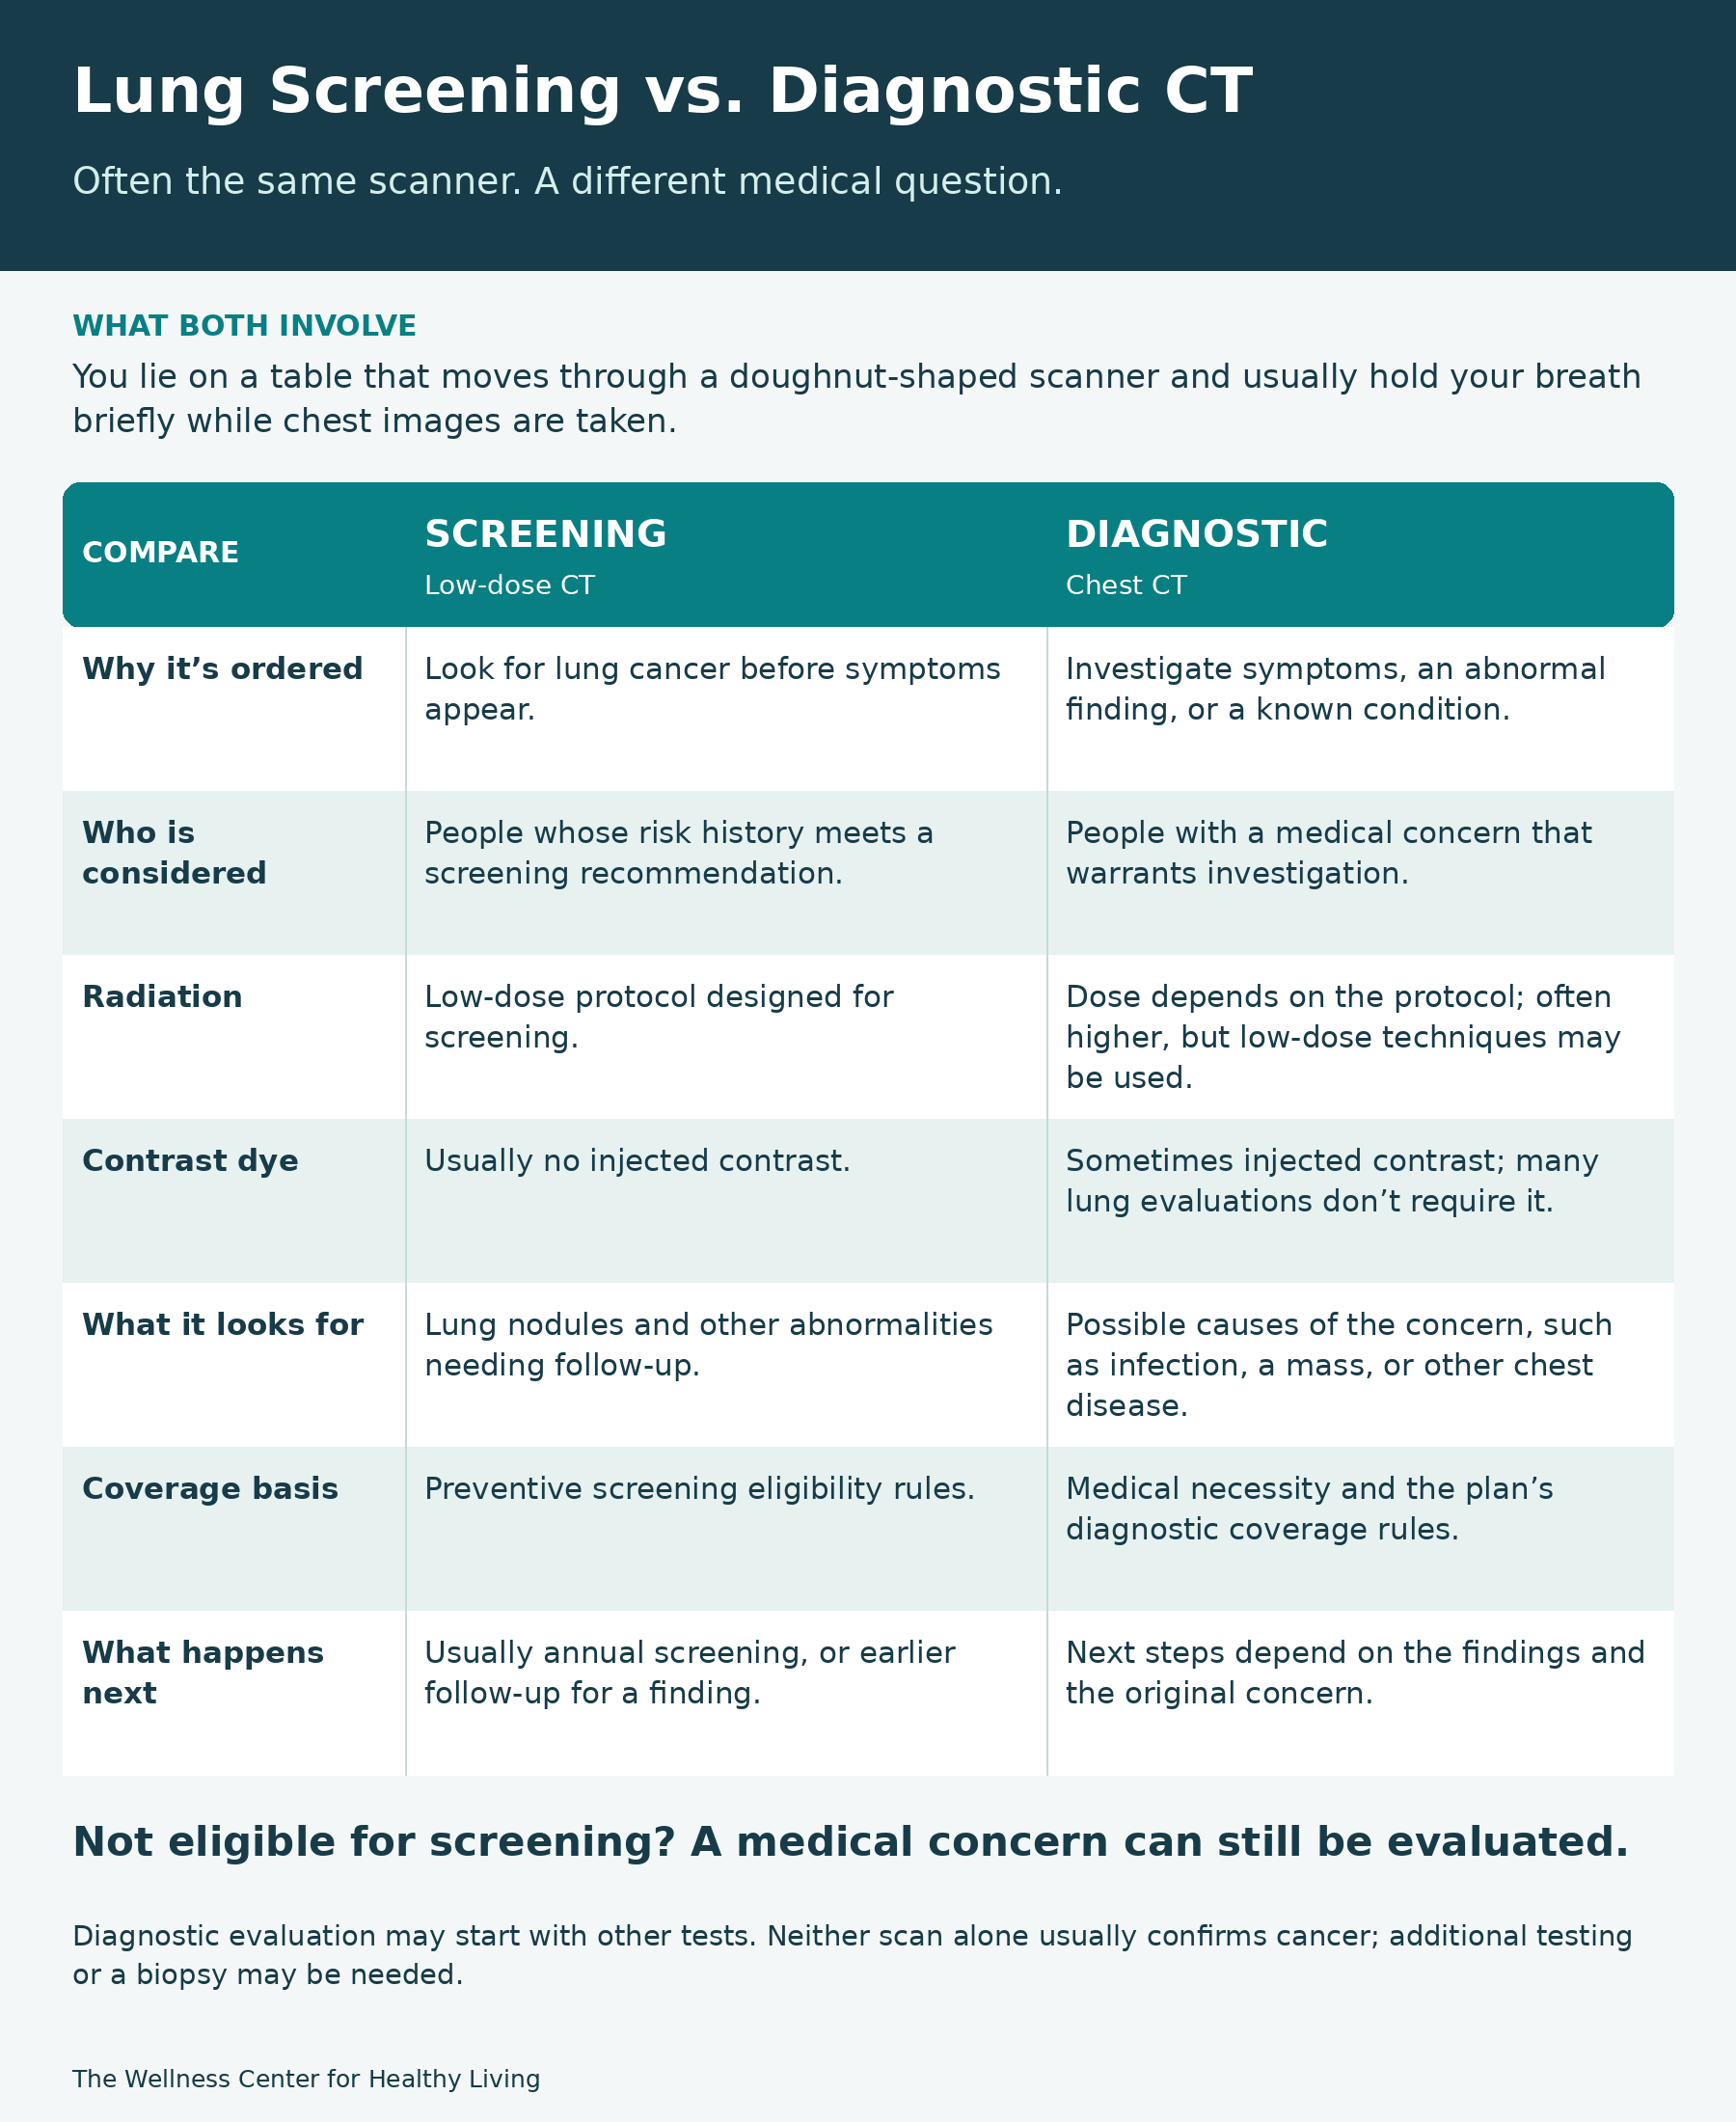
Both pathways can involve a CT scanner. During a chest CT, you lie on a table that moves through a short, doughnut-shaped scanner and usually hold your breath briefly while images are taken. Screening uses a low-dose protocol, generally without injected contrast. A diagnostic CT’s protocol depends on the medical question and may or may not involve contrast.


Diagnostic evaluation doesn’t always begin with a CT. Your clinician decides which examinations or tests are appropriate.


Most importantly, you don’t have to qualify for preventive screening to have a medical concern evaluated. The American Cancer Society advises people with possible lung cancer symptoms to seek medical assessment; testing in that situation is diagnostic rather than screening. 


Comparison of screening and diagnostic chest CT scans, including purpose, eligibility, radiation, contrast, and coverage.

Can insurance cover diagnostic testing?


Yes, diagnostic testing can be covered even when preventive screening isn’t.


Medicare Part B covers diagnostic tests, including CT scans, when a provider orders them to investigate or treat a medical problem and the testing is medically necessary. The preventive lung screening age and smoking criteria don’t determine eligibility for every diagnostic chest CT. www.medicare.gov


However, coverage doesn’t necessarily mean no cost. Under Original Medicare, the Part B deductible and coinsurance generally apply, with costs varying by setting and supplemental coverage. Other plans have their own coverage and payment requirements. www.medicare.gov


A symptom also doesn’t automatically mean a CT is needed. The clinician evaluates the concern and chooses appropriate testing.


This leaves an important difference: diagnostic evaluation investigates something concerning, while screening tries to find disease before that concern develops.


Changes worth discussing with your doctor


Don’t dismiss a persistent or changing cough, unexplained breathlessness, recurrent respiratory problems, unexplained weight loss, or other concerning changes simply because you never smoked or quit long ago.


These changes have many possible causes. They deserve assessment rather than assumptions. If you have symptoms that might indicate lung cancer, seek medical advice rather than waiting to become eligible for screening. www.cancer.org


Useful questions include:


  • What’s my smoking history in pack-years?
  • Which screening recommendation applies to me?
  • Does my insurance use different eligibility criteria?
  • Does my family history or other medical history change the assessment?
  • If I have a symptom or abnormal finding, what evaluation makes sense?
  • Are research studies available for people outside standard screening criteria?

Why I think Hawai‘i should pay attention


The two gaps deserve separate consideration.


For former smokers like me, the issue is the difference between recommendations and coverage. For Asian women who’ve never smoked, it’s whether smoking-based eligibility overlooks people whose risk deserves further study.


I’d like to see Hawai‘i participate in research and discussion about carefully designed screening approaches for higher-risk people outside current criteria. Such efforts would need reliable follow-up and a way to assess benefits, costs, and unnecessary procedures.


My own position is clearer now than when I first wrote about this topic. My 1996 quit date excludes me from Medicare’s national preventive screening coverage. It doesn’t automatically exclude me from the American Cancer Society’s recommendation.


For Asian women who’ve never smoked, the FANSS finding provides a concrete reason to investigate further: researchers found invasive cancers in women whom smoking-based screening rules leave out.


Being outside screening criteria isn’t the same as being without risk. Understanding that distinction helps you ask a more useful question: what does my history mean for me, and what should happen next?


A Note from Marsha


I’m glad I quit smoking in 1996. Learning about screening didn’t change that. It changed my understanding of how medical recommendations and insurance coverage can differ.


It also reminded me why I keep researching. A rule can be useful without answering every question about an individual’s health. I want TWC to help you understand those distinctions, recognize what remains uncertain, and have a more informed conversation about your own situation.


Take Control of Your Health!

Where You Might Want to go Next


When Understanding Doesn’t Fit in the Appointment Slot
Why important health questions sometimes need more time than a medical appointment allows.


When Health Information Changes: What Should You Ask?
Questions to help you understand changing health messages, research, and recommendations.


Are We Measuring Healthspan the Wrong Way?
A closer look at what we measure when we talk about living longer and staying healthy.


Share This:

Person reviewing health insurance paperwork after a denied medical claim.
By Marsha Sakamaki • October 13, 2026
When health insurance denies care or payment, patients face more than medical bills. Explore the financial, emotional, and practical costs of fighting back.
Light-wood infrared sauna cabin with a glass door; shelves of folded towels stand beside it.
By Marsha Sakamaki • October 11, 2026
Explore how infrared sauna relates to skin health through circulation, heat response, sweating, research, and changes Marsha has observed in herself and clients.
Older woman in her late 60s lifts a light dumbbell during a seated strength exercise in a bright hom
By Marsha Sakamaki • October 11, 2026
Learn how creatine supports muscle energy, what research shows about strength in older adults, and what to know about dosing, weight changes, kidney tests, and more.
Person applying white cream to their cheek, with more cream visible on their forehead, nose, and chi
By Marsha Sakamaki • October 7, 2026
Care for aging skin without complicated routines. Learn how gentle cleansing, moisturizing, and sun protection support your skin's comfort and protective barrier.
By Marsha Sakamaki • October 7, 2026
How politics shapes health messaging, research funding, and what we're able to know
Older woman practicing acoustic guitar while reading sheet music in a sunlit room.
By Marsha Sakamaki • October 5, 2026
Discover how cognitive reserve supports brain resilience, with six practical ways to strengthen thinking and support cognitive health as you age.
Glass bottle of golden castor oil beside castor beans, leaves and seed pods.
By Marsha Sakamaki • October 5, 2026
Explore 42 castor oil uses for skin, hair, castor oil packs, massage and digestive support, with research, tradition and practical guidance.
By Marsha Sakamaki • October 3, 2026
Seafood mislabeling can affect your health, your wallet, and your sourcing choices. Learn what a Honolulu study found and which questions help you buy fish.
Older woman studying books and writing in a notebook beside a laptop in a bright home study.
By Marsha Sakamaki • October 3, 2026
Explore the strengths of the aging brain, how knowledge differs from processing speed, and practical ways to keep learning and using your experience.
Older woman holding a question sheet while discussing a medical report with a clinician.
By Marsha Sakamaki • October 3, 2026
Why medical appointments can leave questions unanswered, and how shared education could give patients and clinicians more room for understanding.